

Could this be perimenopause if I still have periods?
Yes. Perimenopause is the transition before menopause, and periods can continue throughout these changing years. The ovaries change their production of estrogen and progesterone, and cycles become less predictable. A period may arrive earlier, later, or with a different flow. Hot flashes, night sweats, sleep trouble and mood changes can appear before periods stop. You do not have to wait for your final period to discuss symptoms that are affecting your everyday life.
The transition often starts in the 40s. The sources describe different age ranges: Cleveland Clinic says the mid-40s is usual, while the National Institute on Aging says most women begin between 45 and 55. These ranges describe groups of people; they do not tell you what is happening in your own cycle. Earlier changes deserve a conversation rather than an automatic label.
Menopause is confirmed after 12 months without a period or spotting. During the transition, the useful questions are what has changed, how much it affects you, and whether another cause needs attention. At Viva Centers in Doral, an assessment with Gissella Rivera can begin with those questions. Bring the concern that matters most to you, even if you are unsure which stage applies.
What do the early and late transition stages mean?
The STRAW+10 framework describes reproductive aging through changes in menstrual patterns. In the early transition, cycle lengths persistently differ by seven days or more. The key is a recurring difference in the length of cycles, rather than one unexpected date. You may still have periods, but the spacing no longer follows the pattern you were used to. A record can help you describe that change without trying to assign yourself a stage.
The late transition begins with a gap of at least 60 days without a period. This stage lasts about one to three years on average, and hot flashes are likely. A long gap does not by itself confirm that periods have ended permanently. Another period may still occur during perimenopause, and pregnancy remains possible. Bring the actual dates rather than assuming that a missed period answers every question.
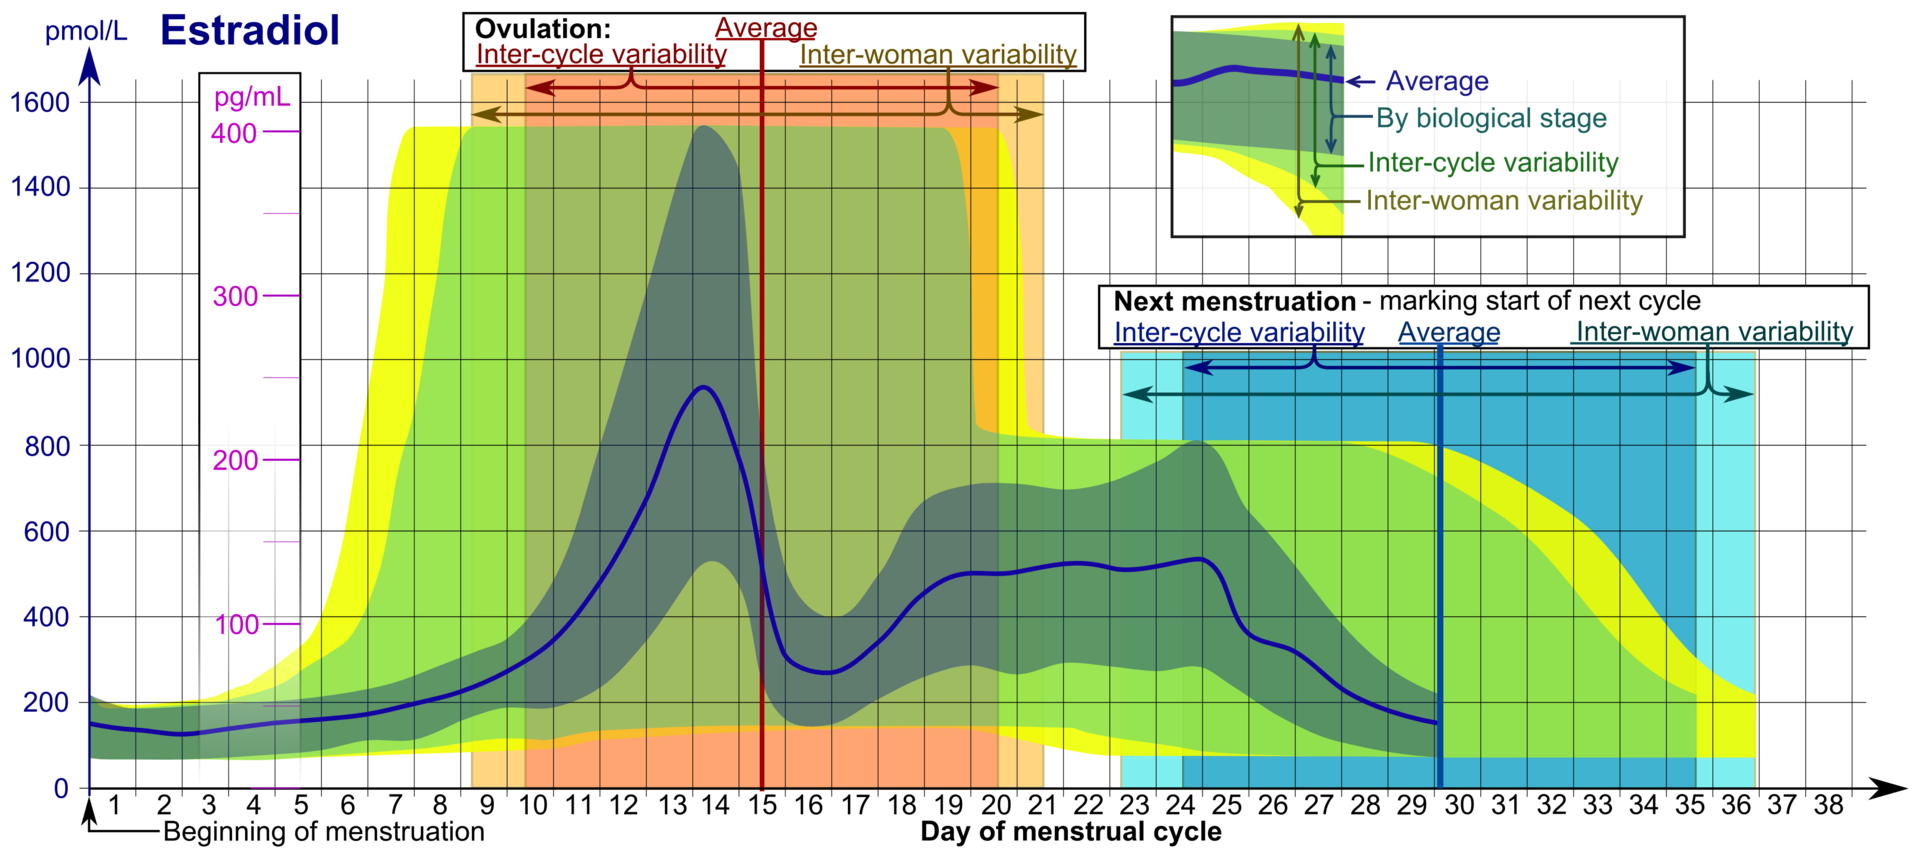
STRAW+10 is intended to apply across ages, ethnic backgrounds, body sizes and lifestyles. It gives the care team a shared way to describe the transition; it is not a timetable for your symptoms. If the calendar and your symptoms seem to tell different stories, discuss both. The goal of the visit is to understand your pattern and care needs, not to make every experience fit a single chart. The estradiol chart shows one normal ovulatory cycle; it is not a perimenopause test and not a way to assign yourself a stage.
How long might this transition and the hot flashes last?
There is no single end date that fits everyone. Cleveland Clinic describes an average perimenopause duration of about four years, with some transitions reaching eight years. STRAW+10 gives a shorter estimate of one to three years for the late transition specifically. These numbers describe different parts of the journey. An estimate for the late stage should not be used as the expected length of the entire transition.
The SWAN study answers a different question: how long frequent hot flashes or night sweats last. It found a median duration of 7.4 years in total, including 4.5 years after the final period. A median is the middle of the durations measured in that study. It is not a personal prediction, and it does not mean that every person has frequent symptoms for that many years.
This distinction matters when you ask whether a symptom should already be over. Hot-flash duration and the years of changing periods are not the same measurement. Your care plan can focus on the symptoms you have now and be revisited as your cycle changes. Tell Gissella Rivera whether you are mainly worried about unpredictable bleeding, interrupted nights, or the uncertainty itself, so the conversation starts with your priorities.
Are heavier or closer periods part of the transition?
Periods can become shorter, longer, lighter, heavier or skipped during perimenopause. ACOG advises reporting bleeding changes even though changing cycles are common. For context, NICHD describes most adult menstrual cycles as 21 to 35 days, with an average of 28 days. That general range is background information, not a reason to dismiss a new change in your own usual pattern.
Some patterns need assessment: periods less than 21 days apart, bleeding between periods or after sex, large clots, very heavy flow, or a period lasting several days longer than usual. Cleveland Clinic also advises a visit if you need to change pads or tampons every one to two hours. Describe the flow in practical terms, including how often you change protection and whether the bleeding interrupts work, sleep or leaving home.
Changing hormones are not the only possible explanation. The evidence pack lists infections, fibroids, polyps, clotting problems and cancer among causes of concerning bleeding. This list does not say which cause you have. FIGO provides a framework for describing abnormal bleeding and investigating its cause. At Viva, the starting point is assessment and a plan for the next step, with gynecologic evaluation coordinated when appropriate.
What should I write down before my appointment?
Bring a simple record of what you have noticed, if you have one. Write down the first and last dates of bleeding, the spacing between periods, and whether the flow seems lighter or heavier than usual. Include spotting between periods or after sex. The transition stages depend on patterns over time, while the bleeding warning signs depend on details that a general label such as irregular may leave out.
You can also note nights interrupted by sweats, hot flashes during the day, mood changes, and vaginal symptoms you want to discuss. Add a few words about the effect on daily life rather than trying to give every symptom a score. For example, you might want help with waking repeatedly, being surprised by another period, or feeling unlike yourself. These notes are preparation for a conversation, not a home diagnostic test.
Bring your current medicine and contraception list and your questions about pregnancy plans. You do not need a perfect calendar or several months of notes to request a visit. Concerning bleeding should be reported when it happens. If you have only a few dates, start there. Gissella Rivera can review the information available and discuss whether assessment, selected tests, symptom care or a referral is the next step.

Why might one hormone blood test leave me without an answer?
A single hormone result often cannot identify this transition because hormone levels fluctuate. Cleveland Clinic describes hormone tests as unreliable for diagnosing perimenopause for that reason. STRAW+10 notes that follicle-stimulating hormone, or FSH, can move between normal and menopausal ranges during the late transition. A result that looks different from what you expected does not replace the story of your changing cycles and symptoms.
NICE guidance says that otherwise healthy women aged 45 or older can be identified as being in perimenopause from symptoms and menstrual changes without laboratory testing. It considers FSH testing for people aged 40 to 45 with symptoms, or under 40 when menopause is suspected. Those age-related recommendations are not instructions to order a panel yourself. They explain why the testing conversation can differ from one person to another.
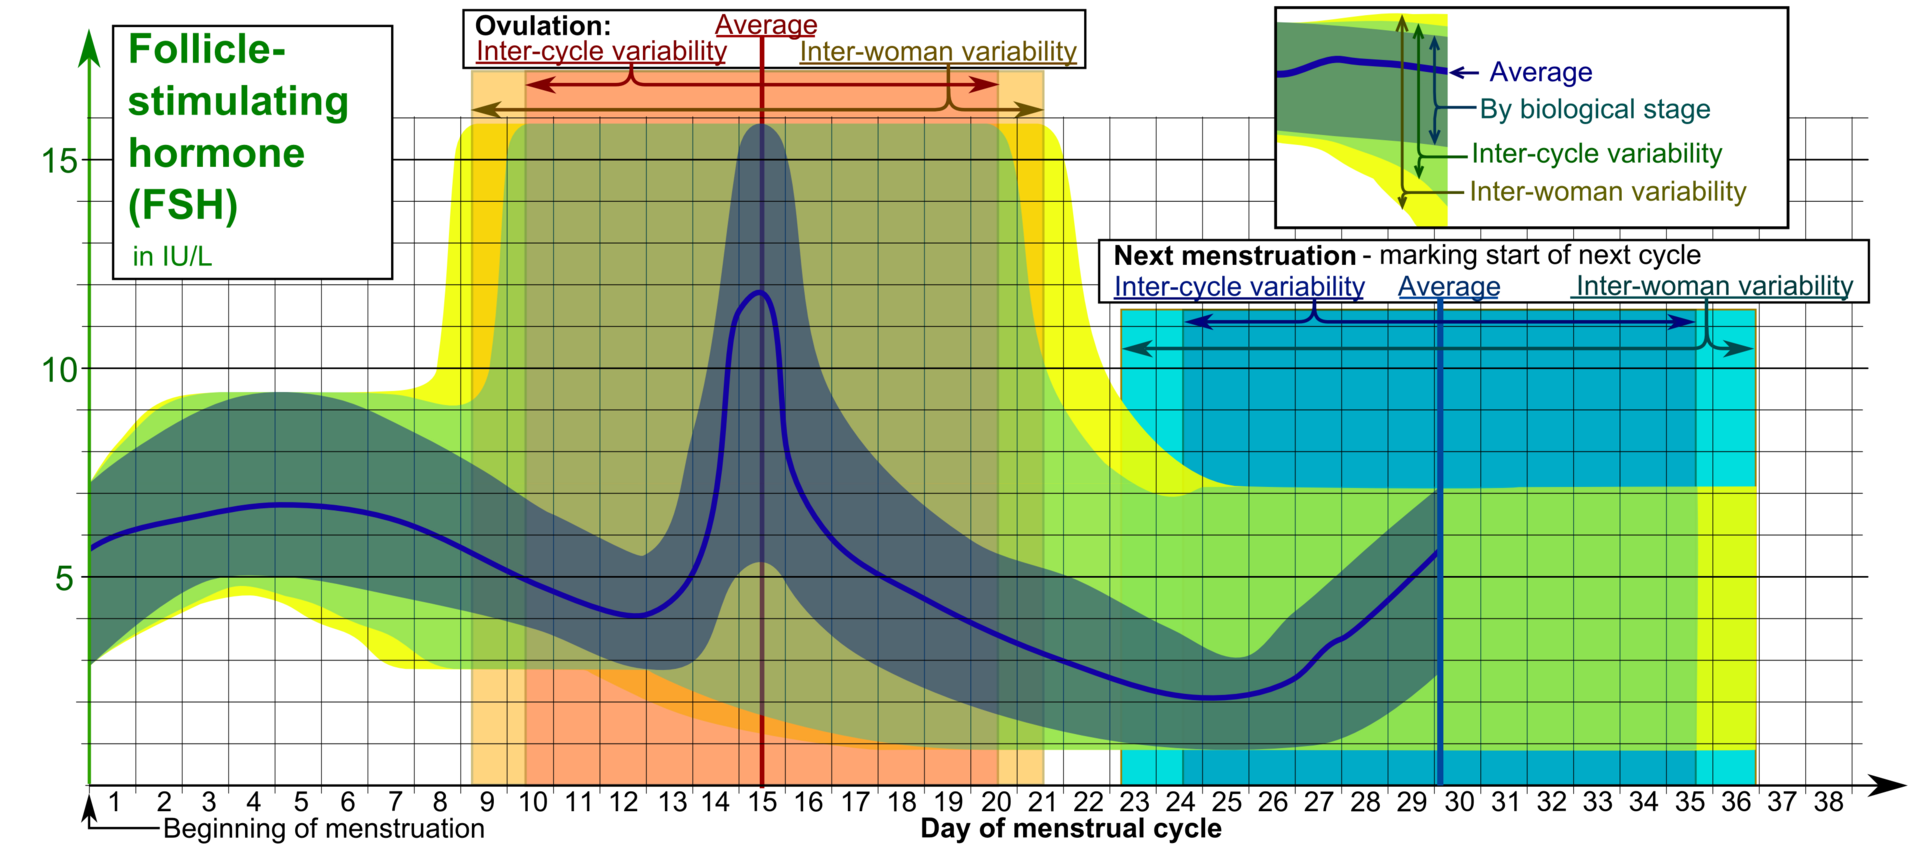
At a visit, ask what question a proposed test is meant to answer and how the result would affect the plan. Selected laboratory testing can be discussed when another condition needs investigation; that is different from promising that one number will confirm every symptom. The chart shows the usual rise and fall of FSH across one ovulatory cycle, with a peak around ovulation. It is a picture of a typical cycle, not a cutoff and not a way to read your own result. In the late transition, FSH can be in the menopausal range one day and in the normal range another day, which is why one blood test often cannot confirm perimenopause.
Can I still get pregnant, and what about contraception?
Yes, pregnancy is still possible during perimenopause. Irregular or widely spaced periods do not mean that ovulation has ended. Cleveland Clinic advises assuming that ovulation may still happen until 12 months have passed without a period. The National Institute on Aging advises continuing birth control for at least 12 months after the last period if pregnancy is not wanted. Discuss your own stopping plan rather than using one missed cycle as the signal.
Your pregnancy goals belong in the symptom-care conversation. Tell Gissella Rivera whether you want to avoid pregnancy, are considering it, or are unsure. Ask how your current contraception fits with the symptoms and bleeding changes you want to address. The evidence pack includes hormonal birth control among approaches used for symptoms during this transition. Choosing an approach requires an individual discussion, rather than assuming that the same option suits every person.
Ask separately about pregnancy prevention and symptom relief when reviewing a proposed plan. Bring the name of your current method and any concerns about continuing it. If your periods are difficult to track, say so; the uncertainty is part of the conversation. A visit can address contraception alongside hot flashes, sleep and bleeding, while keeping fertility questions visible instead of treating them as a concern only for younger years.
What if sleep, mood changes or migraines are my main concern?
Sleep trouble and mood changes can occur while you are still menstruating. The perimenopause review in the evidence pack describes changes in sleep, mood, bleeding and vaginal symptoms as concerns that can affect quality of life before menopause. Hot flashes and night sweats are also common. You can ask for help based on the effect on your day, without waiting for all of these concerns to appear together.
Tell Gissella Rivera whether your main difficulty is interrupted sleep, irritability, feeling low, or concentrating on everyday tasks. Brain fog is among the symptoms described in the pack. Describe what has changed for you rather than assuming that every difficult day has a hormonal explanation. Persistent low mood deserves care. The assessment can begin with your experience and move to a discussion of the appropriate next step.
If migraines are part of your health history, bring that history and your questions to the visit as well. Ask how it should be considered when discussing your care options. You can ask for a separate assessment of a headache concern rather than assuming that its timing explains its cause. Your symptom list can include concerns that need their own assessment, even when they happen during the same years as menstrual changes.
Could another ovarian or cycle condition explain the changes?
Irregular cycles are not specific to perimenopause. The evidence includes PCOS, also called PMOS in some sources, and premature ovarian insufficiency, or POI, among other cycle conditions. Fibroids and polyps can also be involved in abnormal bleeding. Ask for an explanation of the possibilities that fit your history rather than treating a symptom list as proof of one condition. The linked sources introduce these concepts; they do not diagnose you.
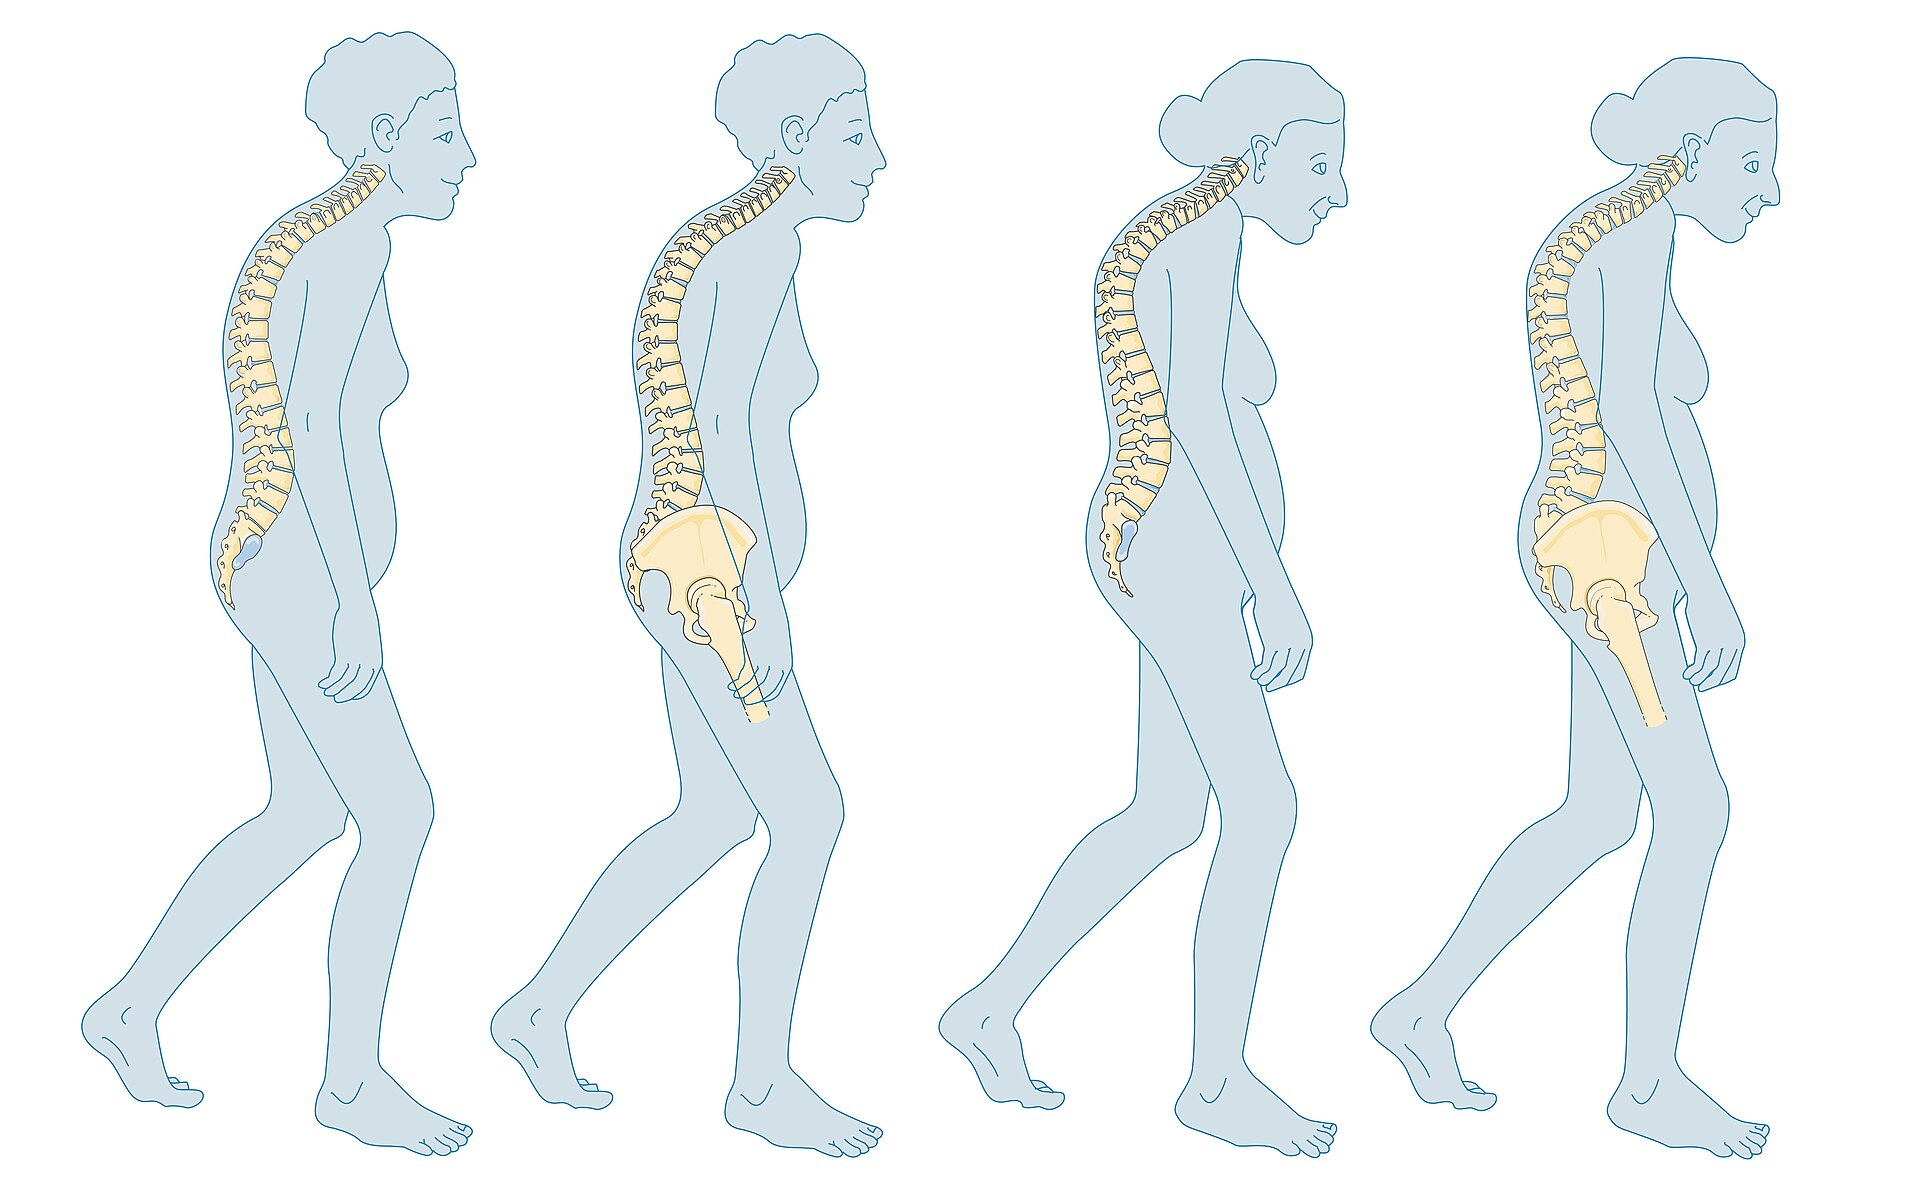
PCOS/PMOS can involve irregular or absent periods, signs of higher androgens such as extra hair, and ovarian follicle changes. POI means that the ovaries stop working normally before age 40; periods and pregnancy may still occur. Its effects can include fertility, bone and heart concerns. That is why a younger person with menstrual changes should not simply assume the usual midlife transition. If this is premature ovarian insufficiency, hormone therapy can reduce many effects on bones, heart and well-being, unless a cancer history rules it out. The bone drawing is a general picture of osteoporosis, not a picture of your bones.
The pack also describes cycle changes associated with stress, weight loss or excessive exercise through hypothalamic causes. If you have a thyroid history, bring it and ask whether it belongs in the assessment. At Viva, Gissella Rivera can discuss selected testing and coordinate gynecologic or other specialty evaluation when the question needs further assessment.
Sources
- 2023 International Evidence-based Guideline for the Assessment and Management of Polycystic Ovary Syndrome (recommendations)
- Evidence-based guideline: premature ovarian insufficiency (ESHRE)
- Functional hypothalamic amenorrhea: an Endocrine Society clinical practice guideline
- About Polycystic Ovary Syndrome (PCOS)
- About Primary Ovarian Insufficiency (POI)
- Polyendocrine metabolic ovarian syndrome (PMOS), previously called polycystic ovary syndrome
- Perimenopause: age, stages, signs, symptoms and treatment
- The two FIGO systems for normal and abnormal uterine bleeding symptoms and classification of causes of abnormal uterine bleeding in the reproductive years: 2018 revisions
What can I try in daily life while we discuss treatment?
You can start with practical comfort measures while discussing the symptoms that need more help. The National Institute on Aging suggests dressing in layers, using a fan and keeping the bedroom cool. Its advice also includes avoiding alcohol, spicy foods and caffeine, stopping smoking and keeping a healthy weight. Choose changes that you can explain and revisit at your appointment rather than turning the whole day into a checklist.
Healthy eating and regular activity are part of the advice in the evidence pack. Calcium and vitamin D intake are discussed for bone health, and NICE includes keeping muscle strength through physical activity. These recommendations support broader health. The nonhormone position statement finds limited evidence for exercise, yoga and acupuncture specifically as hot-flash treatments. Staying active should not be presented as a promise that it will stop your hot flashes.
If symptoms continue to affect you, discuss other options. Having tried a fan or a cooler room does not settle which treatment is appropriate. The evidence also does not support herbal remedies and supplements as dependable hot-flash treatment, and some can cause harm. Bring any supplements you use to the conversation. Your plan can combine practical daily adjustments with clinically discussed options and follow-up, according to the symptoms you want to address.
How are contraception-based approaches discussed during this stage?
Hormonal birth control is one of the approaches described for symptoms during perimenopause. The first question is what you want the plan to accomplish: avoiding pregnancy, addressing symptoms, or discussing both. Bring your current method and tell Gissella Rivera whether you are satisfied with it. You can ask about contraception-based approaches before periods stop, while keeping the bleeding changes themselves part of the assessment.
The evidence on PCOS/PMOS provides a separate example: combined hormonal pills may be used for cycle control when pregnancy is not wanted. That example applies to the condition discussed in those sources. It is not proof that your irregular periods are PCOS/PMOS, or that the same approach is appropriate for every person in perimenopause. Different reasons for changing cycles need to remain distinct when reviewing options.
Ask how an option fits your health history, what symptom it is intended to address, and what follow-up will involve. Also ask what to do if the bleeding remains troublesome. Your symptoms and preferences can guide the care conversation. At Viva, the discussion can include hormonal and non-hormonal choices, prescribing when appropriate, and a referral when further evaluation is needed. A plan should leave you knowing which question each part is meant to address.
When might hormone therapy help, and what risks need review?
Hormone therapy may be discussed during perimenopause when appropriate. It is the most effective treatment for hot flashes and can help vaginal and urinary symptoms. The choice is individualized, with attention to your symptoms, health history and preferences. Treatment guidance describes a generally favorable balance for eligible women under 60 or within 10 years of menopause, but that age range does not by itself establish that hormones are suitable for you.
Systemic estrogen can be given in different forms. If you have a uterus, a progestogen is also needed to protect its lining. Local vaginal estrogen is an option for vaginal dryness. Systemic hormone therapy is usually not recommended with a history of breast or endometrial cancer, stroke, heart attack, blood clots or liver disease, or during pregnancy. Tell Gissella Rivera about these histories before considering a plan.
Risks include a small increase in breast cancer with combined therapy, and a small increase in stroke and blood clots with systemic therapy. Non-pill forms may carry less clot risk. In the WHI trial, postmenopausal women with a uterus who took estrogen plus progestin had higher rates of coronary heart disease, breast cancer, stroke and blood clots in the lung than the placebo group. Those trial results are not your personal risk number. Do not use hormone therapy to prevent heart disease, breast cancer or dementia. Tailor the plan, use the lowest effective dose, and review it at least once a year.
Sources
- The 2022 hormone therapy position statement of The North American Menopause Society
- Treatment of Symptoms of the Menopause: An Endocrine Society Clinical Practice Guideline
- Risks and benefits of estrogen plus progestin in healthy postmenopausal women: principal results from the Women's Health Initiative randomized controlled trial
- Hormone Therapy for Menopause (FAQ)
- Perimenopause: age, stages, signs, symptoms and treatment
What options are available if I prefer to avoid hormones?
Non-hormone options can be discussed if hormones are unsuitable or you prefer another approach. The 2023 nonhormone position statement supports certain non-hormone prescription medicines, including a class that acts on the brain’s temperature center, for hot flashes. It also supports cognitive-behavioral approaches and clinical hypnosis. These are options described by the sources, not a statement that every service is available at Viva Centers.
The discussion should begin with the symptom you want to address. For vaginal dryness, non-hormonal moisturizers and lubricants are options; local vaginal estrogen is a hormonal option that can be discussed separately. A treatment aimed at hot flashes is not automatically the answer to unpredictable bleeding or every sleep concern. Ask what each proposed option is intended to help and when to return for review.
Herbal remedies and supplements do not have dependable support for hot flashes in this evidence pack, and some carry risks such as liver damage. Natural wording on a label is not evidence of benefit. Bring a list of what you use and ask about it. At Viva, Gissella Rivera can discuss hormonal and non-hormonal choices, prescribe when appropriate, and coordinate further care. Your preferences can guide the conversation while benefits, limitations and risks remain visible.
What happens at a visit, and when should I seek urgent help?
A visit with Gissella Rivera at Viva Centers can start with your cycle pattern, symptoms and the concern that brought you in. Bring available dates, your medicine and contraception list, relevant history, and questions about pregnancy. The conversation can cover selected tests, lifestyle steps, contraception-based approaches, hormone therapy or non-hormone choices when appropriate. Agree on what needs follow-up and what change should prompt earlier contact. Booking begins the assessment; it does not establish a diagnosis.
Persistent abnormal bleeding or a question about early ovarian-function changes may need gynecologic or other specialty evaluation. Viva assesses, discusses care and coordinates referrals; outside imaging or procedures require arrangements with the receiving service. Book with Gissella Rivera through the appointment option on this page. You can bring a partial record; concerning bleeding should not wait while you collect more dates.
Promptly request assessment for very heavy flow, large clots, protection changes every one to two hours, bleeding between periods or after sex, periods less than 21 days apart, or bleeding after 12 months without a period. These warnings apply even when other symptoms seem consistent with perimenopause. Review the urgent guidance below for situations that may require emergency care rather than a routine booking.
Sources
- What Is Menopause?
- Management of the perimenopause
- Perimenopause: age, stages, signs, symptoms and treatment
- The Menopause Years (FAQ)
- Evidence-based guideline: premature ovarian insufficiency (ESHRE)
- The two FIGO systems for normal and abnormal uterine bleeding symptoms and classification of causes of abnormal uterine bleeding in the reproductive years: 2018 revisions
Studies & sources
- The 2022 hormone therapy position statement of The North American Menopause Society
Menopause (journal); The North American Menopause Society (now The Menopause Society) · 2022
Hormone therapy is the most effective hot-flash treatment and should be individualized with regular review.
- The 2023 nonhormone therapy position statement of The North American Menopause Society
Menopause (journal); The North American Menopause Society · 2023
The statement supports selected non-hormone prescriptions, cognitive-behavioral approaches and clinical hypnosis for hot flashes.
- Treatment of Symptoms of the Menopause: An Endocrine Society Clinical Practice Guideline
The Journal of Clinical Endocrinology & Metabolism; Endocrine Society · 2015
Screen heart and breast-cancer risk before hormone therapy. Evidence does not support using it to prevent heart disease, breast cancer or dementia.
- Risks and benefits of estrogen plus progestin in healthy postmenopausal women: principal results from the Women's Health Initiative randomized controlled trial
JAMA · 2002
In the WHI, estrogen plus progestin in postmenopausal women with a uterus raised coronary heart disease, breast cancer, stroke and lung-clot risk compared with placebo.
- What Is Menopause?
National Institute on Aging (NIH) · 2024
Pregnancy prevention remains relevant, with birth control advised for at least 12 months after the last period if pregnancy is not wanted.
- Hot Flashes: What Can I Do?
National Institute on Aging (NIH) · 2021
NIA describes practical cooling measures and cautions that herbal hot-flash remedies are unproven and may carry risks.
- Hormone Therapy for Menopause (FAQ)
American College of Obstetricians and Gynecologists (ACOG) · 2024
Systemic hormone therapy requires an individualized risk review, and a progestogen is needed with estrogen when a uterus is present.
- Menopause: identification and management (NICE guideline NG23)
National Institute for Health and Care Excellence (NICE), UK · 2015
NICE supports identifying perimenopause without laboratory tests in otherwise healthy women aged 45 or older with symptoms and menstrual changes.
- Menopause (health topic)
MedlinePlus, U.S. National Library of Medicine · 2026
Menopause is confirmed after 12 months without periods, with earlier cessation needing attention to age.
- Executive summary of the Stages of Reproductive Aging Workshop + 10 (STRAW+10)
The Journal of Clinical Endocrinology & Metabolism · 2012
STRAW+10 describes persistent cycle-length differences of at least seven days in early transition and gaps of at least 60 days in late transition.
- Duration of menopausal vasomotor symptoms over the menopause transition (SWAN)
JAMA Internal Medicine · 2015
SWAN found a median duration of 7.4 years for frequent hot flashes or night sweats, including 4.5 years after the final period.
- Management of the perimenopause
Clinical Obstetrics and Gynecology · 2018
The review describes bleeding, sleep, mood and vaginal symptoms that can affect quality of life before menopause.
- Perimenopause: age, stages, signs, symptoms and treatment
Cleveland Clinic · 2024
Perimenopause can involve unpredictable cycles while pregnancy remains possible, and hormone fluctuations limit diagnostic blood tests.
- Symptoms of menopause and perimenopause
NHS (UK) · 2026
Changes in periods, sleep, mood and vaginal comfort can occur during the transition, and bleeding after 12 months without a period needs assessment.
- The Menopause Years (FAQ)
American College of Obstetricians and Gynecologists (ACOG) · 2025
ACOG describes fluctuating estrogen and changing periods in the 30s and 40s and advises reporting bleeding changes.
- 2023 International Evidence-based Guideline for the Assessment and Management of Polycystic Ovary Syndrome (recommendations)
Human Reproduction; ESHRE/ASRM/Monash-led international guideline · 2023
The international PCOS guideline includes healthy lifestyle and combined hormonal pills for cycle control when pregnancy is not wanted.
- Evidence-based guideline: premature ovarian insufficiency (ESHRE)
Human Reproduction Open; European Society of Human Reproduction and Embryology · 2024
POI can affect fertility, bones and heart health and requires care distinct from assumptions about the usual midlife transition.
- The two FIGO systems for normal and abnormal uterine bleeding symptoms and classification of causes of abnormal uterine bleeding in the reproductive years: 2018 revisions
International Journal of Gynecology & Obstetrics; FIGO · 2018
FIGO provides standard bleeding terms and a framework for classifying causes of abnormal uterine bleeding.
- Functional hypothalamic amenorrhea: an Endocrine Society clinical practice guideline
The Journal of Clinical Endocrinology & Metabolism; Endocrine Society · 2017
Hypothalamic causes of absent periods can involve stress, weight loss or excessive exercise and require exclusion of other causes.
- About Polycystic Ovary Syndrome (PCOS)
NICHD (NIH) · 2024
PCOS/PMOS can include irregular or absent periods, signs of higher androgens and ovarian follicle changes.
- About Primary Ovarian Insufficiency (POI)
NICHD (NIH) · 2024
POI involves ovarian function changes before age 40 while periods and pregnancy may still occur.
- About Menstruation
NICHD (NIH) · 2024
NICHD describes most adult menstrual cycles as 21 to 35 days with an average of 28 days.
- Polycystic Ovary Syndrome (PCOS) (FAQ)
American College of Obstetricians and Gynecologists (ACOG) · 2025
Combined hormonal pills are an option for cycle control in PCOS when pregnancy is not wanted.
- Polyendocrine metabolic ovarian syndrome (PMOS), previously called polycystic ovary syndrome
NHS (UK) · 2026
The NHS uses PMOS for the condition previously called PCOS and describes irregular periods among its symptoms.